

table of contents
Medicare bundled payment rules set a single target price for an episode of care, typically spanning 30 to 90 days, and hold providers financially accountable for every Part A and Part B service delivered inside that window. Three CMS models define the current landscape: BPCI Advanced, a voluntary program built on 90-day episodes; TEAM, which becomes mandatory for selected hospitals starting January 1, 2026; and CJR-X, a nationwide mandatory joint-replacement model launching January 1, 2028. For hospitals and physician groups, the practical implication is straightforward: reconciliation risk, quality-based payment adjustments, and new data and coordination requirements are no longer optional planning exercises.
TL;DR:
- Hospitals in CMS-selected CBSAs must prepare for TEAM starting January 2026, with a shorter 30-day post-discharge window increasing discharge planning pressure.
- CJR-X will become nationwide mandatory for most IPPS and OPPS hospitals beginning January 2028, leaving little room for opt-out once in scope.
- The core mechanics involve defining episode triggers, building target prices from historical data with regional adjustments, and conducting semi-annual reconciliations with risk caps around 20 percent.
- Successful participation requires accurate episode-level data, aligned clinical pathways, financial reserves for potential losses, and robust technology and staffing frameworks.
- Financial and operational risks include delayed settlements, inaccurate attribution, care coordination failures, and increased scrutiny over beneficiary choice and quality reporting.
How Do Medicare Bundling Rules Work Across CMS Models?
Bundled payments replace piecemeal fee-for-service billing with a single accountability target for an entire episode of treatment. Instead of every provider submitting claims and getting paid independently, CMS tracks total spending against a benchmark and reconciles the difference, either rewarding efficient, high-quality care or clawing back payment when costs run high. Four models currently define how this works in practice, and each one applies to a different slice of the provider population.
BPCI Advanced is the voluntary option still active for hospitals and physician groups willing to take on episode risk in exchange for flexibility. It uses 90-day Clinical Episodes, retrospective reconciliation against a target price, and requires participants to use Certified Electronic Health Record Technology (CEHRT). Payment ties directly to quality performance, and the model qualifies as an Advanced Alternative Payment Model (APM) under MACRA, which matters for physician groups trying to avoid MIPS reporting burden. BPCI Advanced originally covered 29 inpatient clinical episodes plus several outpatient episodes, giving participants a menu of conditions to select rather than an all-or-nothing commitment.
TEAM, the Transforming Episode Accountability Model, is where the ground shifts under providers who assumed bundling would stay optional. TEAM is mandatory for acute care hospitals paid under the Inpatient Prospective Payment System (IPPS) that sit within 188 selected Core-Based Statistical Areas (CBSAs), and it runs from January 1, 2026 through December 31, 2030. The model covers five surgical episode types with a 30-day post-hospitalization window, a considerably tighter timeline than BPCI Advanced’s 90 days. That shorter window changes everything about discharge planning; there’s far less room to absorb a slow-moving skilled nursing facility (SNF) placement or a delayed home-health start. TEAM also pushes more administrative weight onto hospitals directly, rather than letting a convener organization manage the risk on their behalf.
CJR-X extends that same mandatory logic to lower-extremity joint replacement (LEJR) episodes, but at a much larger scale. Set to begin January 1, 2028, CJR-X requires participation from most hospitals paid under IPPS and the Outpatient Prospective Payment System (OPPS), with CMS projecting more than 2,500 hospitals nationwide will be pulled in. It replaces the original voluntary Comprehensive Care for Joint Replacement (CJR) model, and CJR-X’s certification documents point to refined target-pricing methodology as the reason regulators expect steadier program savings than earlier joint-replacement bundles delivered.
Legacy BPCI, the original four-model framework CMS launched over a decade ago, is worth knowing even though it’s no longer active for new participants. Here’s how those models differed, and why later versions moved away from parts of the original design:
- Model 1 bundled only the inpatient hospital stay, leaving physician and post-acute payments untouched, which limited its ability to change coordination behavior.
- Model 2 extended the episode through post-acute care, using retrospective reconciliation against a historical baseline, a structure that became the template for TEAM and CJR-X.
- Model 3 started the episode at post-acute care admission rather than hospital discharge, aimed at skilled nursing and rehab facilities that wanted to lead episode management themselves.
- Model 4 used prospective, lump-sum payment made directly to the hospital at admission, shifting cash-flow timing dramatically compared with the retrospective models.
The shift from Model 1’s narrow scope to TEAM’s broader, shorter-window, mandatory structure tells you where CMS policy is heading: tighter episodes, less voluntary opt-out room, and heavier reliance on target-pricing refinements that reduce the design flaws earlier bundles struggled with.
What Are the Mechanics Behind Target Prices and Reconciliation?
Every bundled payment model runs on the same underlying machinery, even though the details shift from program to program. Understanding that machinery is what separates a hospital that models its risk accurately from one that gets blindsided at reconciliation.
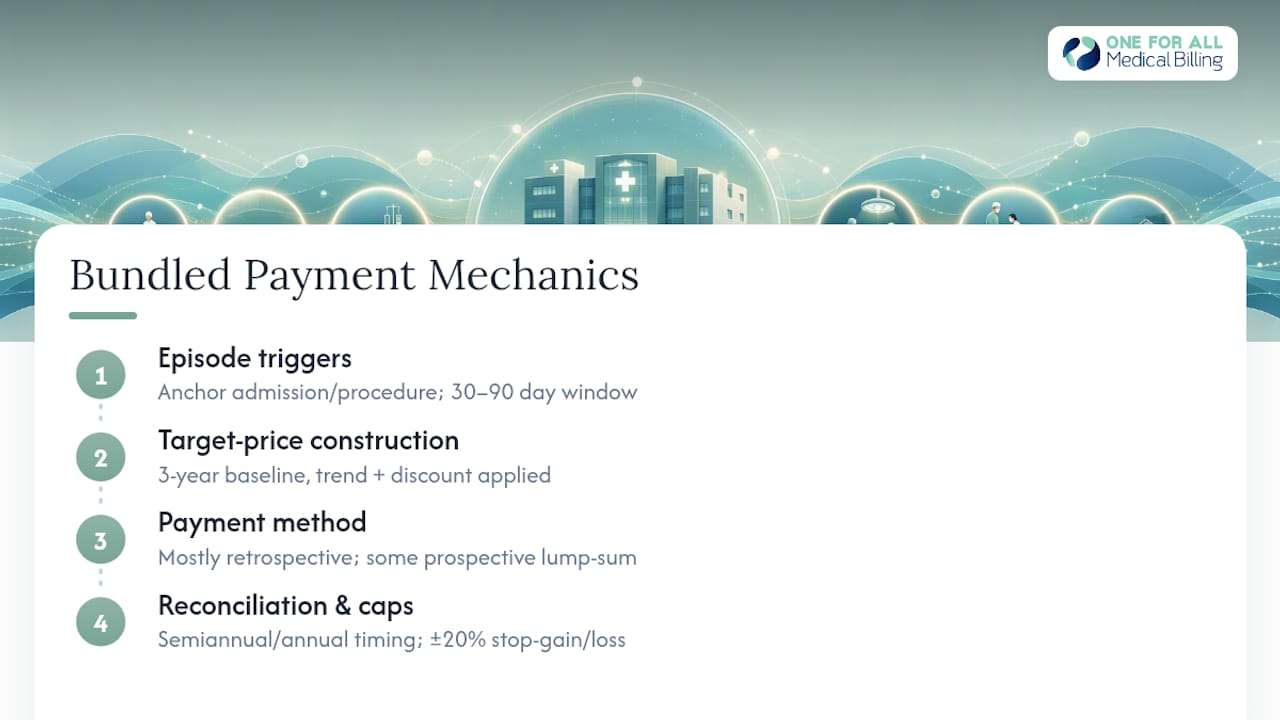
Episode triggers and windows. An episode starts at an anchor event, either an anchor hospitalization (the admission itself) or an anchor procedure (a specific surgical code), and CMS defines exactly which claims count toward the episode from that point forward. Everything billed under Part A and Part B during the episode window, physician visits, SNF stays, home health, durable medical equipment, and readmissions related to the episode, gets counted against the target price. Bundled payment episodes typically run 30 to 90 days depending on the model, and that window length directly determines how much post-discharge spending a hospital is on the hook for.
Target-price construction. CMS builds the benchmark from a historical baseline, typically pulling three years of claims data for the relevant episode type and geography, then applies trend factors to account for changes in medical practice and inflation. A discount factor, often a set percentage below the projected benchmark, gets subtracted before the final target price is set. That discount is CMS’s built-in savings mechanism: providers only break even if they beat a price that’s already discounted below expected spending. BPCI Advanced and CJR-X both use variations of this three-year baseline approach, though CJR-X’s refined methodology adjusts for regional cost variation more aggressively than the original CJR model did.
Prospective vs. retrospective payment. Most current models use retrospective reconciliation: providers get paid normally through fee-for-service claims throughout the episode, and CMS compares total actual spending to the target price afterward. If actual spending comes in under target, the provider receives a reconciliation payment. If spending exceeds target, the provider owes money back. A smaller number of historical models, like BPCI’s original Model 4, used prospective lump-sum payment instead, paying the full bundled amount upfront and letting the hospital manage disbursement to other providers directly.
Reconciliation timing and risk caps. CMS typically reconciles bundled episodes semi-annually or annually, depending on the model, which means providers can carry unresolved financial exposure for months before knowing their true performance. To limit how much any single provider can lose, CMS sets stop-gain and stop-loss limits, commonly around plus or minus 20 percent of the target price, with lower caps often applied to rural and safety-net hospitals to protect facilities with thinner operating margins. The net figure after reconciliation is often called the Net Payment Reconciliation Amount (NPRA), and a negative NPRA means the hospital repays CMS directly.
Pro Tip: Run your own reconciliation simulation using at least 24 months of historical claims before your model’s performance period starts. Providers who wait until the first live reconciliation cycle to find out their exposure almost always discover it too late to correct course.
Attribution rules determine which organization gets credit, or blame, for an episode. In physician group practice (PGP) attribution, the episode gets assigned based on the attending or operating National Provider Identifier (NPI) on the claim that triggered the anchor event, following a defined precedence order. Accountable Care Health (ACH) attribution, used in hospital-based models like TEAM and CJR-X, generally attributes the episode to the hospital where the anchor admission or procedure occurred. Certain beneficiaries get excluded from attribution altogether, including those enrolled in Medicare Advantage, those with end-stage renal disease under specific circumstances, and patients who die during the episode window before key benchmarks apply. Getting attribution wrong, especially in multi-site systems where several NPIs touch the same patient, is one of the most common sources of reconciliation disputes.
Which Hospitals Fall Under Mandatory vs. Voluntary Bundling?
The line between “this affects us” and “this doesn’t” has gotten a lot less forgiving. TEAM is mandatory, not optional, for any acute care hospital paid under IPPS that falls within one of the 188 selected CBSAs CMS has designated for the model. There’s no opt-out based on hospital size or system affiliation once a facility sits inside a covered CBSA. CJR-X goes even further: it applies to most hospitals paid under IPPS and OPPS nationwide starting in 2028, regardless of CBSA, making it one of the broadest mandatory bundling requirements CMS has ever rolled out.
A handful of exemptions and transition rules matter for planning purposes:
- Hospitals already participating in TEAM are exempt from CJR-X obligations until their TEAM participation period concludes, preventing double-counted risk on overlapping episode types.
- Hospitals below certain claims-volume thresholds may face adjusted reconciliation requirements rather than full exposure, though this doesn’t eliminate participation entirely.
- BPCI Advanced remains fully voluntary throughout, giving hospitals and physician groups outside mandatory CBSAs a way to build bundling experience on their own timeline.
- Facilities that close, merge, or change ownership status during a model performance period trigger specific transition rules that CMS evaluates case by case.
Here’s the timeline that matters most for internal planning:
- January 1, 2026: TEAM begins for hospitals in selected CBSAs, running through December 31, 2030.
- 2026 through 2027: The window most hospitals outside TEAM’s immediate scope have to build internal readiness before CJR-X arrives.
- January 1, 2028: CJR-X becomes mandatory nationwide for most IPPS and OPPS hospitals.
- Ongoing: Reconciliation cycles occur semi-annually or annually depending on the model, meaning financial results from early performance periods won’t be final for months after each episode closes.
The practical takeaway is this: if your hospital sits in one of the 188 TEAM CBSAs, readiness work needed to start yesterday. If you’re outside that list but paid under IPPS or OPPS, you have roughly two years before CJR-X arrives, and two years is not a long runway once you factor in data system upgrades, staff training, and post-acute network development. Waiting until the performance period starts to figure out your target-price exposure is the single most common and most expensive mistake administrators make with mandatory models.
How Should Providers Prepare for Bundled-Payment Participation?
Readiness for bundled payments isn’t a single project, it’s four parallel work streams that need to run at the same time because they depend on each other. Here’s the order that actually works, based on how these models are structured.
- Build episode-level data and analytics first. Before anything else, construct dashboards that track spending against a simulated target price for each relevant episode type. Pull historical claims data and run reconciliation stress tests using different discount-factor assumptions, so you know roughly where you’d land under TEAM or CJR-X rules before you’re legally required to.
- Align clinical coordination around the episode window. Map out discharge planning pathways with your preferred SNF and home-health partners, and formalize those relationships rather than relying on ad hoc referrals. Build telehealth and post-discharge visit protocols that keep patients engaged without requiring costly in-person follow-up for every touchpoint. A remote patient monitoring strategy fits naturally here, since post-discharge monitoring directly affects episode spending during the reconciliation window.
- Set financial preparedness in motion early. Establish a reconciliation reserve fund sized to your worst-case stop-loss exposure, not your best-case projection. Model out what a negative NPRA looks like under the roughly 20 percent stop-loss cap, and get any gainsharing or distribution agreements with post-acute partners reviewed by legal counsel before the performance period begins, not after a dispute arises.
- Shore up technology and staffing gaps. Confirm your CEHRT setup meets the specific requirements of whichever model applies to you, since BPCI Advanced and CJR-X both tie participation eligibility to certified technology use. Strengthen coding accuracy and HCC risk-adjustment practices, because inaccurate risk coding distorts your benchmark calculation before the episode even starts. Assign dedicated care managers to episode oversight, and clarify internally whether your organization functions as a convener, coordinating episodes across multiple sites, or as an individual episode initiator (EI) managing its own risk directly.
Pro Tip: Cap internal gainsharing distributions until your organization has passed at least one full reconciliation cycle without a negative NPRA. It’s tempting to distribute projected savings early, but a single bad quarter under a mandatory model can turn projected gains into real losses if reserves aren’t protected first.
None of these four work streams function well in isolation. A hospital with excellent discharge coordination but no reconciliation reserve is still exposed. A hospital with strong data analytics but weak SNF partnerships will still see episode costs creep upward from avoidable readmissions. Treat readiness as a single coordinated build, not four separate checklists running on different timelines.
What Risks Do Bundled Payments Create, and How Do You Manage Them?
The retrospective structure most bundled models use creates a cash-flow problem that catches a lot of finance teams off guard. Providers keep getting paid fee-for-service throughout the episode, then find out months later, at semi-annual or annual reconciliation, whether they owe money back. That gap between service delivery and financial certainty means a hospital can look profitable on a monthly basis while quietly accumulating reconciliation debt that shows up as a painful surprise at settlement.

Operational risk compounds the financial exposure. Post-acute coordination failures, a SNF placement that runs longer than expected, a home-health referral that falls through, or a readmission that wasn’t flagged early, all drive episode spending above target without anyone noticing until claims data catches up weeks later. Data gaps make this worse: if your systems can’t track episode-level spending in near real time, you’re reconciling blind. Incomplete or incorrect attribution, especially in systems where multiple NPIs touch the same patient across different departments, creates disputes that eat administrative time and delay payment resolution.
There’s also a policy dimension worth taking seriously. Bundled models raise legitimate concerns about beneficiary choice and access. If financial incentives push providers toward the cheapest post-acute option rather than the most clinically appropriate one, that’s a compliance problem as much as a quality problem. Regulatory scrutiny around care denial or steering has increased as mandatory models have expanded, and providers need documentation showing that referral decisions are driven by clinical appropriateness, not solely by episode economics.
Mitigation comes down to a few concrete moves:
- Run conservative, worst-case reconciliation simulations rather than optimistic projections, so reserve funds are sized for reality.
- Adopt a phased approach where possible, testing bundling logic on voluntary episodes through BPCI Advanced before mandatory models force full participation.
- Formalize gainsharing agreements with post-acute partners in writing, with clear terms on how savings and losses get distributed.
- Bring legal and compliance review into the process early, particularly around beneficiary choice documentation and referral patterns.
Earlier evaluations of Medicare’s bundled-payment initiatives found consistent reductions in post-acute care spending across LEJR episodes, which is genuinely good news for the model’s core premise. But those same evaluations flagged mixed net program savings under early voluntary designs, largely because target-pricing methodology hadn’t caught up to real-world variation yet. That’s precisely why CJR-X arrived with refined pricing logic rather than a simple copy-paste of the original CJR model.
What Waivers and Quality Measures Affect Reconciliation?
CMS builds specific waivers into bundled-payment models to let providers redesign care without tripping over standard Medicare payment rules that assume a fee-for-service world. Three waivers show up repeatedly across models:
- The 3-day SNF rule waiver removes the standard requirement that a patient spend three consecutive inpatient days before Medicare covers a SNF stay, letting providers move patients to appropriate post-acute settings faster.
- Telehealth waivers expand which services can be delivered remotely during the episode window, reducing the need for in-person follow-up visits that add cost without necessarily improving outcomes.
- The post-discharge home-visit waiver allows certain home-visit services that wouldn’t normally qualify for separate Medicare payment, supporting closer monitoring right after discharge when readmission risk is highest.
CJR-X’s certification documentation confirms these waivers apply with specific operational conditions attached, and BPCI Advanced has used comparable waiver structures throughout its performance periods. If your organization is building telehealth pathways to support episode management, it’s worth reviewing current telehealth billing requirements alongside the model-specific waiver rules, since general Medicare telehealth policy and bundled-model waivers don’t always align perfectly.
Quality measures aren’t a side note in bundled payments, they directly adjust how much reconciliation payment a provider actually receives. CMS calculates a Composite Quality Score (CQS) using a defined set of quality metrics relevant to each episode type, and that score scales the reconciliation amount up or down. A hospital that hits its target price on cost but performs poorly on quality metrics can still see reconciliation payment reduced, which is exactly the incentive structure CMS designed: cost efficiency alone doesn’t earn full reward.
Post-episode monitoring policy exists to prevent a specific type of gaming: providers delaying necessary care until just after the episode window closes, shifting cost outside the bundle without actually reducing total patient need. CMS tracks average 30-day spending patterns immediately following episode end to detect unusual spikes that suggest care was postponed rather than eliminated. Providers with a pattern of low in-episode spending followed by a spike right after the window closes can expect additional scrutiny.
For the full technical specifications, CMS’s model pages house the official rules for each program, while OACT certification documents provide the actuarial sign-off required before mandatory models like CJR-X can proceed. Both are worth bookmarking, since CMS updates episode definitions and waiver terms periodically as models mature.
A Publisher’s Perspective on Getting Bundled-Payment Ready
We’ve spent more than 20 years handling revenue cycle management for practices and hospitals navigating exactly this kind of regulatory shift, and we maintain a 90% clean claim rate across the specialty billing work we do. What strikes us most about TEAM and CJR-X is how much they punish organizations that treat billing accuracy as a back-office afterthought rather than a strategic input to episode pricing.
Reconciliation modeling, coding precision, and HCC risk adjustment aren’t separate from bundled-payment readiness, they’re the foundation of it. A benchmark built on inaccurate historical claims data sets a target price that’s wrong before the episode even begins. CEHRT integration and clean coding aren’t compliance checkboxes here; they’re what determines whether your reconciliation comes back positive or negative. Providers who wait for their first mandatory performance period to discover this connection are already behind.
— One For All Medical Billing
Let One For All Medical Billing Help You Prepare for Bundled-Payment Risk
One For All Medical Billing gives hospitals and physician groups the reconciliation modeling, coding accuracy, and CEHRT-aligned workflows that mandatory bundling models like TEAM and CJR-X now demand, without the guesswork of building that infrastructure from scratch.

With more than 20 years of specialty-focused revenue cycle management experience and a 90% clean claim rate, One For All Medical Billing works with practices ranging from single-site clinics to large multi-site health systems on exactly the kind of episode-level accuracy that bundled payments require. Strong HCC risk adjustment and precise coding directly affect your target-price benchmark, and reconciliation support means fewer surprises when settlement periods arrive. For a closer look at how outsourced RCM pricing works for organizations preparing for mandatory participation, review current billing service pricing models. If your hospital sits inside a TEAM-covered CBSA or is planning ahead for CJR-X in 2028, visit Oneforallmed to request a readiness assessment and get a clear picture of where your reconciliation exposure stands today.
FAQ
What Are the CMS Guidelines for Bundling Payments?
CMS guidelines set a single target price for an episode of care, typically 30 to 90 days, covering Part A and Part B services, with reconciliation against that benchmark handled semi-annually or annually depending on the specific model, such as TEAM or BPCI Advanced.
What Are the Downsides of Bundled Payments?
The main downsides are retrospective reconciliation risk that creates cash-flow uncertainty for months after care is delivered, operational strain from coordinating post-acute partners, and the potential for financial incentives to affect beneficiary referral choices if not properly monitored.
What Are the CMS Incident-to-Billing Guidelines for 2026?
Incident-to billing guidelines govern how services performed by non-physician practitioners under a supervising physician’s direction get billed, and they operate separately from bundled-payment episode rules; providers should confirm current supervision and documentation requirements directly through CMS’s published billing guidance rather than assume bundling rules override them.
What Is the 21-Day Rule for Medicare?
There is no standard rule defined in current Medicare bundled-payment policy; providers may be thinking of specific SNF coverage timelines or model-specific episode windows, which vary by program, so it’s worth confirming the exact policy reference against official CMS model documentation rather than assuming a universal rule.
Is Participation in Medicare Bundled-Payment Models Mandatory?
It depends on the model and your hospital’s location: TEAM is mandatory for IPPS hospitals in 188 selected CBSAs starting in 2026, CJR-X becomes mandatory nationwide for most IPPS and OPPS hospitals in 2028, and BPCI Advanced remains fully voluntary.

